Planning a Pregnancy After a Chromosomal Miscarriage

Genetics advice, early scans and NIPT

What the NHS offers at each stage

When tests have shown that a miscarriage was caused by a chromosome change, planning the next pregnancy usually comes down to three questions: what the result means for the future, how early the baby can be checked on a scan, and which screening or diagnostic tests suit you.

Most chromosome changes in a miscarriage happen by chance and are unlikely to happen again. This page explains the NHS pathway step by step, and how our genetic counsellors and fetal medicine specialists can support it.

Where you are starting from

What a chromosomal result tells you about next time

Chromosome changes are the commonest cause of early miscarriage. Around half of early losses happen because the pregnancy developed with the wrong number or arrangement of chromosomes, and in most cases this happens by chance while both parents' own chromosomes are normal. That does not make the loss any easier, but it is useful information when you plan what comes next.

On balance, it is also encouraging. UK guidance on repeated miscarriage from the Royal College of Obstetricians and Gynaecologists (RCOG) notes that a chromosome change found in a miscarriage is linked to a better outlook in the following pregnancy than a miscarriage in which the chromosomes were normal. Age still counts, and this may not apply where a parent carries a chromosome rearrangement, so the exact finding matters.

According to the NHS, you can try again once your miscarriage symptoms have gone and you feel ready, and most women who have miscarried later have a successful pregnancy. The rest of this page works through three questions that can help you plan.

A scientist working at computer screens in a genetics laboratory, with analysis instruments in the foreground
The laboratory report from the previous test is the starting point for planning.

Question 1

Have you spoken with a genetics specialist?

A genetic counsellor or clinical geneticist can turn a laboratory report into a plan. Ideally this happens before you try again, but it is still worthwhile early in a new pregnancy. Bring the written report from the previous test, because the exact wording matters.

01

What exactly was found?

'Chromosomal' covers several different findings: an extra chromosome (a trisomy), a missing one (a monosomy, such as monosomy X), a whole extra set (triploidy), or a piece of chromosome that is missing, extra or rearranged. Each has a different meaning for the future. Our guide to understanding your result explains the terms.

02

Chance or inherited?

Trisomies, monosomies and triploidy usually arise by chance and are not passed down. Trisomies become more common as the egg-provider gets older, but they do not usually mean that either partner has a chromosome problem. An unbalanced rearrangement is different, because it sometimes comes from a parent who carries a balanced version without knowing it.

03

Does either of you need a chromosome test?

Often not. UK guidance (RCOG, 2023) recommends offering a karyotype, a blood test of both partners' chromosomes, when the pregnancy tissue showed an unbalanced structural rearrangement. After a chance trisomy it is not routinely needed, though European guidance (ESHRE) suggests deciding case by case, for instance where there is a family history of chromosome conditions. See parental karyotyping.

04

Could it happen again?

Most chance chromosome changes are unlikely to happen again. After a miscarriage with a trisomy, one North American laboratory study of later prenatal tests found a trisomy that can continue in pregnancy, such as Down's syndrome, about 1.8 times as often as expected for the mother's age.

The starting chance is low for most people (for Down's syndrome, about 1 in 900 at age 30, at 16 weeks of pregnancy, according to the NHS screening programme), so the overall chance usually stays low, and screening is available.

If one of you carries a balanced rearrangement, further miscarriage is more likely, but most couples still have a healthy baby. In a large Dutch study quoted by the RCOG, 83 in 100 carrier couples had a healthy child, much the same as couples with repeated miscarriages who were not carriers (84 in 100), although carriers more often had another miscarriage (49 in 100, against 30 in 100). A pregnancy with the unbalanced form continuing into the second trimester was uncommon, at under 1 in 100.

By type of finding

How the previous finding can shape the next pregnancy

A general guide only. Your own report, age and history may change what applies, which is why a genetics review is worthwhile.

Previous findingUsually inherited?Parents tested?Points for the next pregnancy
Trisomy (an extra chromosome)No. Usually chance, and more common as the egg-provider gets olderNot usuallyNHS screening, with genome-wide NIPT as an option; diagnostic testing if a result is higher chance
Monosomy X (one X chromosome instead of two)No. Usually chanceNot usuallyRoutine NHS screening and scans; discuss anything else on the report with a genetic counsellor
Triploidy (a whole extra set of chromosomes)No. Usually chanceNot usuallyIf it was a partial molar pregnancy, follow the specialist centre's hCG follow-up and its advice on timing; see molar pregnancy
Unbalanced rearrangement (a piece missing or extra)Sometimes. A parent may carry a balanced versionYes, usually offered to bothGenetics referral; if a parent is a carrier, options include CVS or amniocentesis, or IVF with embryo testing (PGT-SR)
Small deletion or duplication, or an uncertain findingDepends on the findingOnly if a genetics team advises itAsk whether it is relevant at all before planning extra tests

Question 2

Would an early look at the baby's anatomy help?

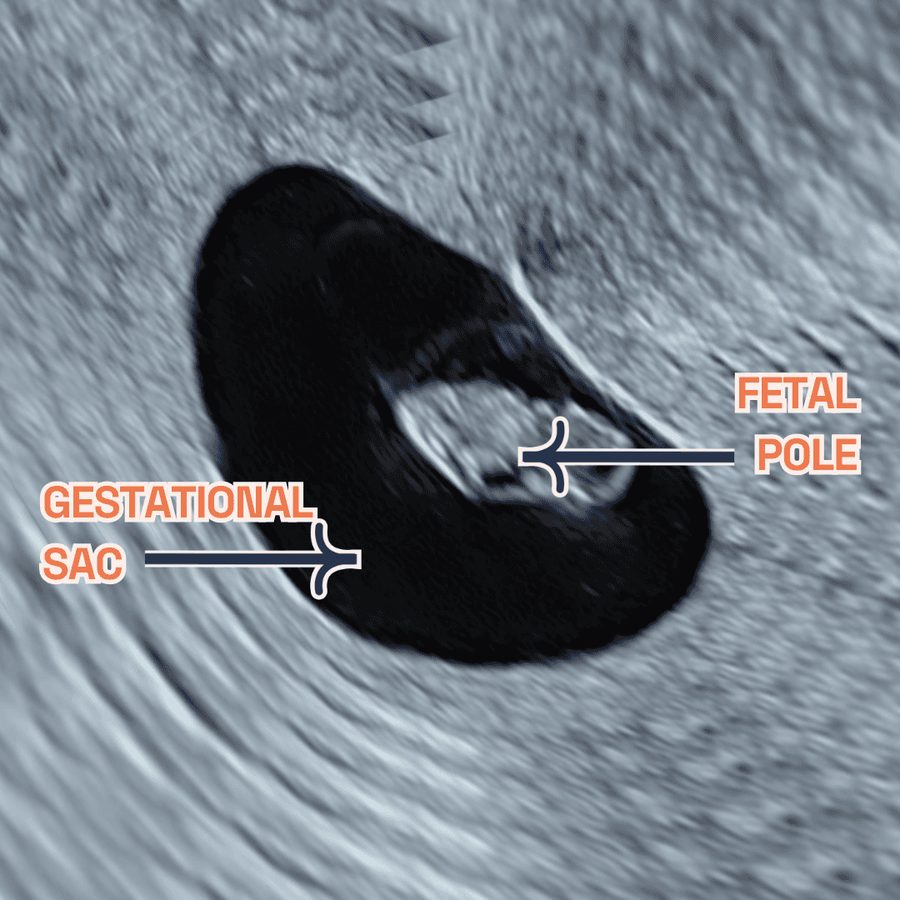
After a loss, many parents want early reassurance that a new pregnancy is developing. A specialist scan at around 10 weeks can examine some major structures that can already be seen by this point. It also confirms the heartbeat, measures the baby to check the dates and shows how many babies there are. It does not replace the 11–14-week and 20-week scans.

There are real limits this early. The skull bones do not usually show clearly until about 11 weeks, and part of the bowel normally sits outside the tummy until around then, so a full check of anatomy is not yet possible. International guidance from ISUOG places the main early anatomy check at 11 to 14 weeks, with many details best seen at around 13 weeks, and some conditions only become visible later in pregnancy.

A scan and a chromosome test answer different questions. Ultrasound shows how the baby is forming but cannot read chromosomes; NIPT screens DNA from the placenta for chromosome changes but cannot show the baby's structure. Scanning before NIPT also confirms a single ongoing pregnancy, which matters because a twin that stopped developing early can affect NIPT results. For these reasons we always perform NIPT together with a scan.

Black-and-white early ultrasound with labels pointing to the gestational sac and the fetal pole
Early scans confirm the heartbeat and dates; a fuller anatomy check follows from 11 to 14 weeks.

Scans in the next pregnancy, and what each can show

Typical timings. If you have pain or bleeding in early pregnancy, your NHS early pregnancy unit can assess you free of charge; later in pregnancy, contact your maternity unit.

WhenScanWhat it can showNHS or private
6–9 weeksEarly viability scanThat the pregnancy is in the womb, the heartbeat and the datesNHS if you have pain or bleeding, and sometimes for reassurance after recurrent miscarriage; otherwise private
Around 10 weeksSpecialist 10-week scanHeartbeat, growth, number of babies and some major structures already visiblePrivate
11–14 weeksDating scan, with the neck measurement if you choose combined screeningDates, and the nuchal translucency used in the combined testNHS, offered to everyone
12–16 weeksEarly fetal scanA more detailed early anatomy check, at the stage when many structures are best seenPrivate
Around 20 weeksMid-pregnancy anomaly scanA detailed anatomy check, including structures that develop laterNHS, offered to everyone

Question 3

NHS screening or genome-wide NIPT?

Every pregnant woman in England is offered screening for Down's, Edwards' and Patau's syndromes (trisomies 21, 18 and 13). A private genome-wide NIPT looks more widely. Both are screening tests: they estimate a chance rather than give a diagnosis.

Offered to everyone

NHS combined test

A blood test between 10 and 14 weeks and a scan measuring the fluid at the back of the baby's neck between 11 and 14 weeks, combined with your age. A result of 1 in 150 or higher counts as higher chance.

After a higher-chance result

NHS NIPT

Offered as a next step after a higher-chance screening result, alongside the choice of a diagnostic test or no further tests. It looks only for trisomies 21, 18 and 13, not other chromosome conditions.

Optional, from 10 weeks

Private genome-wide NIPT

A blood test that also looks at the other chromosomes and, in some tests, for missing or extra pieces of chromosome. See NIPTIFY and our other NIPT options.

Is genome-wide NIPT worth considering after a chromosomal miscarriage?

It can be. Many of the chromosome changes found in miscarriages are something other than an extra chromosome 21, 18 or 13, the only three conditions that NHS screening looks for. A genome-wide test also checks the remaining chromosomes, and some parents find that reassuring after a loss caused by a rarer trisomy.

It also has important limits. When genome-wide NIPT flags a rarer trisomy, the change is often confined to the placenta rather than the baby: in a national Dutch study, only about 6 in 100 such results were confirmed in the baby. Any higher-chance result needs a diagnostic test before decisions are made, and the wait can be stressful. NIPT cannot detect balanced rearrangements, and triploidy can be missed.

Whether it suits you depends on what was found before and how you would use the answer. After a chance trisomy, it may add reassurance alongside NHS screening. If a parent carries a rearrangement, a diagnostic test is often the clearer route; for example, NHS NIPT is not offered to a mother who carries a balanced translocation involving chromosome 21, 18 or 13. Talking it through with a genetic counsellor before booking can make the choice clearer.

We offer NIPTIFY, one of the most comprehensive genome-wide NIPT options currently available privately in the UK, from 10 weeks. The scan is always included, because we do not offer NIPT on its own, and the package costs £690. Alongside whole-chromosome changes, it screens for missing or extra pieces of chromosome larger than about 1 Mb (roughly a million DNA letters).

Screening and testing in numbers

These figures describe groups of people, not any one pregnancy. The sources are listed at the foot of this page.

99.7% Of pregnancies with Down's syndrome picked up by NIPT, with a 0.04% false-positive rate (ISUOG, 2023)
6 in 100 Higher-chance genome-wide NIPT results for rarer trisomies that were confirmed in the baby (TRIDENT-2, 2019)
1 in 150 The NHS cut-off: a combined test result at or above this counts as higher chance
Under 1 in 200 Likely extra miscarriage risk from CVS or amniocentesis by an experienced specialist (RCOG, 2021)

Diagnosis rather than screening

When CVS or amniocentesis may be the better choice

Screening estimates a chance, whereas a diagnostic test examines the baby's chromosomes directly. Chorionic villus sampling (CVS) takes a tiny sample of the developing placenta, usually between 11 and 14 weeks and not before 10 weeks. Amniocentesis takes a small amount of the fluid around the baby, from 15 weeks.

Either test may be worth discussing if a screening result is higher chance, if a parent carries a balanced rearrangement, or if a scan raises a concern. The laboratory can be told about the previous result so that the analysis is planned around it, for example checking specifically for the unbalanced form of a parent's known rearrangement alongside a wider chromosome analysis; your genetics team will advise on what applies to you.

Where a change seen on NIPT or CVS might lie in the placenta rather than the baby, amniocentesis generally reflects the baby's own chromosomes more closely.

When an experienced specialist performs either procedure, the added chance of miscarriage is probably less than 1 in 200 (RCOG); the NHS screening leaflet gives about 1 in 200. After a loss, that can be a heavy number to weigh, and there is no single right answer.

We do not carry out CVS or amniocentesis at London Pregnancy Clinic. If a diagnostic test is being considered, we explain the options and can help you arrange a referral to your NHS fetal medicine unit, where these tests are free when recommended, or to a private fetal medicine consultant. Our amniocentesis guide compares the two procedures.

What to have ready for your first appointments

Whether you see an NHS midwife, a genetic counsellor or our team, these details help the people advising you.

The full laboratory report from the previous test, not only a summary of the result

The dates of any previous losses and how many weeks pregnant you were each time

Any chromosome (karyotype) results for either partner

Letters about hormone (hCG) follow-up, if a molar pregnancy was involved

Results of any recurrent miscarriage tests, such as antiphospholipid or thyroid blood tests

Our services

How we can support your next pregnancy

These options sit alongside your NHS maternity care. Scans take place at our clinics in the City of London and West London, and genetic counselling is by video.

Complex findings

Clinical genetics consultation

A doctor-led appointment with Dr Harry Leitch, Consultant in Clinical Genetics, suited to rearrangements, uncertain findings or a relevant family history. Enquire to book.

10–11 weeks

10-week scan

Heartbeat, growth and a first look at some major structures that can be seen this early. An addition to your 11–14-week and 20-week scans, not a replacement.

Pregnancy after a chromosomal miscarriage: your questions

Does a chromosomal result change when we can try again?

Not usually in itself. The NHS advises trying again when you feel ready and your miscarriage symptoms have gone, and our guide to preparing for your next pregnancy covers timing. Two situations are worth settling first. After a partial molar pregnancy, follow the hCG monitoring and timing advice from the specialist centre. And if a genetics review or parental karyotype has been recommended, having the results before you conceive keeps more options open.

Can a 10-week scan and NIPT replace the NHS scans?

No. ISUOG advises that NIPT should not be used on its own without the scan at 11 to 14 weeks, because a blood test cannot show how the baby is forming. A 10-week scan is an earlier, extra look rather than a substitute. Keep your NHS dating scan and your 20-week anomaly scan, and tell your midwife about any private results.

I am 40 and our last miscarriage was a trisomy. Should I go straight to a diagnostic test?

It is a fair question, and the answer is personal. The NHS screening programme puts the chance of Down's syndrome at around 1 in 100 at age 40, and it may be slightly higher after a trisomic miscarriage. Some people choose screening first and keep diagnostic testing for a higher-chance result; others want a definite answer from the start and accept the small procedure risk. A genetic counsellor can set out the numbers for your age and history before you decide.

One of us carries a balanced translocation. What are our options?

European guidance (ESHRE) describes three main routes: trying again naturally, with the offer of CVS or amniocentesis; IVF with testing of embryos for the rearrangement (PGT-SR); or using donor eggs or sperm. PGT-SR may reduce further miscarriages, but it has not been shown to raise the overall chance of a baby or to shorten the time to pregnancy. A clinical genetics consultation can explain what your specific rearrangement means.

Will the NHS look after me differently this time?

Routine NHS screening is the same for everyone: the dating scan and combined screening between 10 and 14 weeks, then the anomaly scan at around 20 weeks. Extra NHS testing usually follows a specific finding, such as a parent carrying a rearrangement or a higher-chance screening result. After recurrent miscarriage, the RCOG advises supportive care from an experienced team, which may include scans for reassurance.

Tell your midwife about the previous result at booking so it is in your notes, and ask your GP about a genetics referral if the result has never been explained to you.

If the next pregnancy feels frightening

Feeling anxious in a pregnancy after a loss is very common, and early milestones can be hard to enjoy. Miscarriage UK, the working name of the Miscarriage Association, runs a support line (0303 003 6464). Tommy's midwives answer calls free on 0800 0147 800, Monday to Friday, 9am to 5pm. Let your midwife know how you are feeling.

About this information

This page explains general options for a pregnancy after a chromosomal miscarriage; it cannot replace advice about your own situation from your midwife, doctor or genetic counsellor. In any pregnancy, heavy bleeding, severe pain, a fever or feeling faint need prompt attention: contact your early pregnancy unit or NHS 111 straight away, or call 999 in an emergency.

Contact

Talk to us about your next pregnancy

Send us an enquiry

Not for emergencies. If you are bleeding heavily, in severe pain or feel faint, call 999 or go to A&E.

For urgent matters please call 020 3687 2939.

Sources & clinical references

The figures and clinical statements on this page are drawn from the sources below. Guidance evolves — always discuss your individual circumstances with a clinician.

  1. RCOGRecurrent Miscarriage (Green-top Guideline No. 17)2023
  2. Royal College of Obstetricians and GynaecologistsRecurrent miscarriage: patient information2023
  3. NHSMiscarriage2026
  4. Tommy'sRecurrent miscarriage2026
  5. American Journal of Human Genetics (Warburton et al.)Trisomy recurrence: a reconsideration based on North American data2004
  6. ESHRERecurrent Pregnancy Loss guideline, update 20222023
  7. GOV.UK (NHS screening)Screening tests for you and your baby: Down's, Edwards' and Patau's syndromes, combined or quadruple test2026
  8. GOV.UK (NHS Fetal Anomaly Screening Programme)Fetal anomaly screening programme handbook: screening for Down's, Edwards' and Patau's syndromes2026
  9. ISUOG (Ultrasound in Obstetrics & Gynecology)ISUOG Practice Guidelines (updated): performance of 11–14-week ultrasound scan2023
  10. American Journal of Human Genetics (van der Meij et al.)TRIDENT-2: national implementation of genome-wide non-invasive prenatal testing as a first-tier screening test in the Netherlands2019
  11. Royal College of Obstetricians and GynaecologistsAmniocentesis and Chorionic Villus Sampling: Green-top Guideline No. 82021
  12. European Journal of Obstetrics & Gynecology and Reproductive Biology: X (Okoror & Arora)Prenatal diagnosis after high chance non-invasive prenatal testing for trisomies 21, 18 and 13: chorionic villus sampling or amniocentesis? Experience at a district general hospital in the United Kingdom2023