
What Is a Missed Miscarriage, and Why Did It Happen?

Also called a silent or delayed miscarriage

A missed miscarriage means the pregnancy has stopped developing but is still in the womb, as the body has not yet begun to miscarry. There are often no warning signs, so it is usually found on a scan. Here we explain how it is confirmed, why it happens and why genetic testing may still be possible before treatment.

About half of early miscarriages are caused by a chromosome abnormality in the pregnancy, which usually happens by chance and not because of anything either parent did. If you would like to know whether that was the reason, there are more testing options while the pregnancy is still in the womb.

The basics

What is a missed miscarriage?

A missed miscarriage can be one of the most unexpected and upsetting experiences in pregnancy. Unlike many other miscarriages, it often happens without any warning signs, so the news can come as a complete shock. Understanding what it means, how it is diagnosed and what your options are can help you feel a little more prepared for the decisions ahead.

A missed miscarriage, also called a silent or delayed miscarriage or early embryonic demise, is when the embryo or fetus has stopped developing but the body has not yet recognised the loss. None of the usual miscarriage symptoms, such as bleeding, cramping or passing tissue, have happened. 'Missed' refers to this absence of physical signs, which is why the loss usually cannot be detected without a scan.

The pregnancy sac may stay intact, and the placental tissue often carries on producing pregnancy hormones, particularly human chorionic gonadotrophin (hCG). That is why symptoms such as breast tenderness, nausea and tiredness can continue, and why a home pregnancy test may still be positive. In effect, your body still 'thinks' it is pregnant, which can make the diagnosis especially hard to take in.

A woman sitting quietly with a calm, reflective expression
A missed miscarriage often comes as a shock because there were no warning signs

Symptoms

Why there are often no warning signs

The lack of symptoms is what sets a missed miscarriage apart. Many miscarriages begin with vaginal bleeding, cramping or a sudden fading of pregnancy symptoms. With a missed miscarriage there is often nothing obvious at all.

This happens because the body does not immediately register that the pregnancy has stopped developing. Pregnancy hormone levels can stay high for some time, and it can take days or several weeks before they fall far enough for the physical miscarriage to begin. No one yet knows why this delay is short for some people and much longer for others.

Some women say their pregnancy symptoms even seemed to get stronger in the weeks before the diagnosis, which can make the news harder to accept. In the first weeks of the second trimester it may also be too early to feel the baby move, so without bleeding or pain there is no reason to suspect anything is wrong.

There is usually no way you could have known without an ultrasound scan. Not noticing was not a failure on your part, and it was not something you should have detected or prevented.

Diagnosis

How a missed miscarriage is found on a scan

A missed miscarriage is usually found during a routine ultrasound scan, whether that is an early pregnancy scan, the 12-week dating scan or, less often, the 20-week anomaly scan. It can also be found at a non-routine scan, on the NHS or privately, whether or not there are any symptoms.

During the scan, the sonographer or doctor looks for the signs of a developing pregnancy. The key finding in a missed miscarriage is no heartbeat at a stage when one would be expected: the scan shows a pregnancy sac with an embryo or fetus inside, but no flicker of heart activity. The measurements often show that the pregnancy is smaller than expected from your dates or from an earlier scan.

Sometimes the scan shows an empty pregnancy sac, or no clear sac at all. The embryo either did not develop or stopped developing very early and was reabsorbed by the body. You may hear this called early embryo loss, early embryonic demise, anembryonic pregnancy or the older term 'blighted ovum'. Our guide to anembryonic pregnancy explains it in more detail.

When the scan cannot locate a pregnancy inside the womb and no earlier scan has shown one there, the team will consider other explanations, including an ectopic pregnancy, which needs prompt care, and will usually arrange follow-up blood tests (hCG) or scans until the picture is clear.

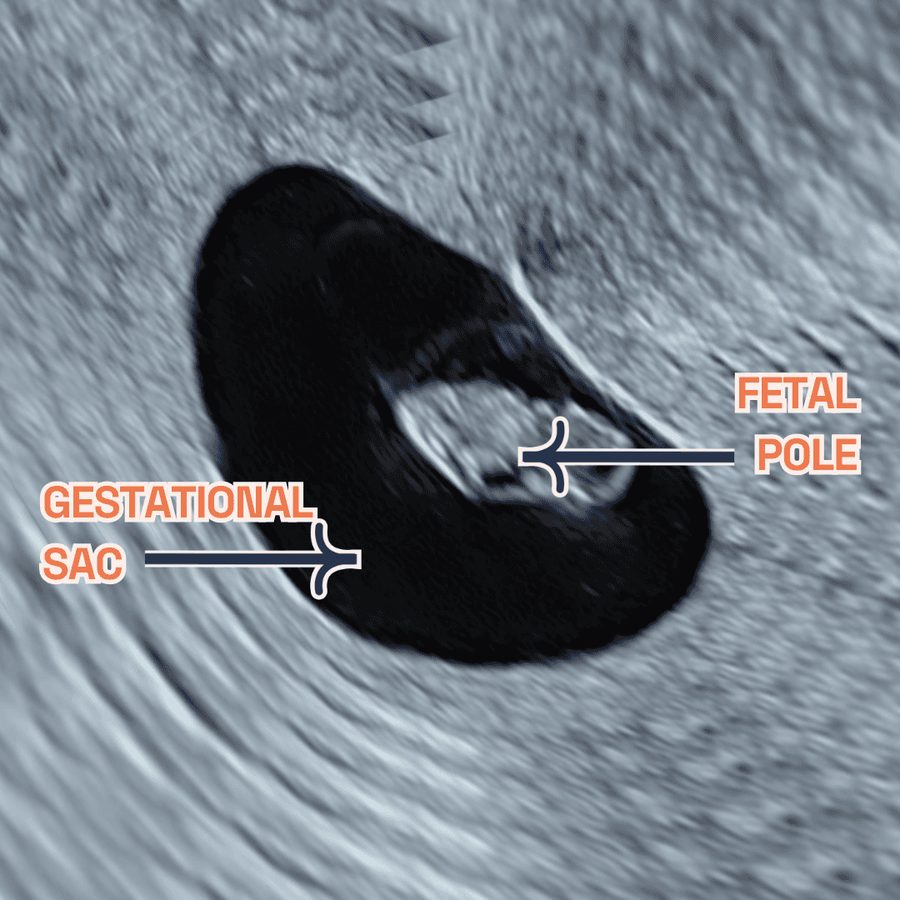
Early pregnancy ultrasound image with the gestational sac and fetal pole labelled
On an early scan, the sac and embryo are measured and the heartbeat is checked

Confirming the diagnosis

How NICE says a missed miscarriage should be confirmed

Diagnosis follows strict guidance designed to prevent one outcome above all: a pregnancy that is still developing being wrongly diagnosed as a miscarriage. NICE guideline NG126 recommends an internal (transvaginal) scan, because it gives the clearest picture, and accepts that a single scan cannot be 100% accurate, especially very early on.

The scan looks for a heartbeat first. If there is none, the next step depends on how long the embryo measures from head to bottom (the crown–rump length, CRL) or, when no embryo can be seen, on the average size of the sac (the mean sac diameter, MSD).

What the scan showsWhat NICE recommends before miscarriage is confirmed
Embryo under 7 mm, no heartbeatRescan after at least 7 days; occasionally more than one rescan is needed
Embryo 7 mm or more, no heartbeatA second specialist opinion, a rescan after at least 7 days, or both
Sac under 25 mm, no embryo visibleRescan after at least 7 days
Sac measuring 25 mm or more, no embryo visibleA second specialist opinion, a rescan after at least 7 days, or both
Abdominal scan only (no internal scan)Record the measurements and rescan after at least 14 days

NICE also says the date of your last period should never be the only guide to whether a heartbeat ought to be seen, and that waiting for the rescan does no harm to the pregnancy.

The wait between scans

In practice, a single scan below these sizes is never enough to diagnose a missed miscarriage, and at or above them a second specialist opinion, a repeat scan or both are still advised. When a repeat scan is needed, it is usually at least a week after the first, to give any continuing development time to show.

These checks exist because early development varies from one pregnancy to another. A pregnancy that looks worrying on one scan may simply be earlier than the dates suggested, or be developing a little more slowly than average but still be healthy.

The wait for that second scan can be extremely stressful. You may find yourself hoping for the best while preparing for the worst, and many people describe it as being 'in limbo'. Mixed and changing emotions are completely normal at this time.

Your NHS early pregnancy unit will arrange any repeat scan you need. If you would like another specialist to look at your pregnancy privately, we offer a second-opinion scan with Dr Fred Ushakov.

Causes

Why does a missed miscarriage happen?

Many missed miscarriages happen because the pregnancy could not develop normally from the very start, rather than because of anything that happened later. The most common identifiable reason is a chromosome abnormality: too many or too few chromosomes, or a piece of a chromosome missing, extra or rearranged. These errors usually happen by chance when the egg or sperm is made or as the fertilised egg first divides, and both parents' own chromosomes are usually normal.

Studies of missed miscarriages find high rates of these changes. In a 2023 study of 1,160 early missed miscarriages from a hospital in China, about 2 in 3 tissue samples had a genetic finding, although in about 1 in 20 samples the change found was of uncertain significance. Many of the women had miscarried before, so the figures may not apply to everyone. The most common single finding was trisomy 16, an extra copy of chromosome 16, followed by trisomy 22 and trisomy 21.

Age plays a part. Errors in egg chromosomes become more common as women get older, so trisomies, and miscarriage overall, become more likely with age. In pooled data published in the Lancet in 2021, about 12 in 100 recognised pregnancies miscarried at ages 20 to 29, about 18 in 100 at 35 to 39 and about 37 in 100 at 40 to 44. Data sets from other countries and decades, using other methods, give different figures, which our miscarriage statistics page compares.

Some chromosome changes do not seem to be linked to age. Monosomy X, where there is a single X and no second sex chromosome, and triploidy, where there are three full sets of chromosomes instead of two, can happen by chance at any age. Our page on chromosomal causes of miscarriage explains each type.

Not every missed miscarriage has a chromosomal cause. Others may be linked to the mother's health or the shape of the womb, and sometimes no cause is found. Why the body takes longer to recognise some losses than others is also not understood.

Missed miscarriage and chromosomes: the figures

These figures describe large groups of pregnancies, not any one person. The studies are listed under sources at the foot of this page.

About 15 in 100 Recognised pregnancies that end in miscarriage, from pooled international data (Quenby et al., Lancet 2021)
About 1 in 2 Early miscarriages due to a chromosome abnormality in the pregnancy, according to RCOG Green-top Guideline 17 (2023)
About 6 in 10 Miscarriages showing a chromosome abnormality when the tissue is tested (Quenby et al., Lancet 2021)
About 2 in 3 Early missed miscarriages with a genetic finding, some of uncertain significance, in a study of 1,160 tissue samples (Xue et al., Scientific Reports 2023)

Was it something I did?

Things that do not cause a missed miscarriage

Many people go over every detail of the weeks before the scan. The evidence is reassuring: in most cases, a missed miscarriage is not caused by anything you did or didn't do. For a fuller look at causes and common worries, read Why did I miscarry?.

  • Exercise and normal physical activity do not cause miscarriage.
  • Having sex, including in early pregnancy, does not cause miscarriage.
  • Ordinary work, including full-time work, and everyday lifting and carrying do not cause miscarriage.
  • Everyday stress and worry have not been clearly shown to cause miscarriage.
  • Smoking and drinking alcohol in pregnancy are linked with a higher risk of miscarriage, and high caffeine intake may be too, although that link is less certain. A small amount of alcohol drunk before you knew about the pregnancy is very unlikely to explain your loss.

Genetic testing

Can a missed miscarriage be tested for a genetic cause?

Finding out whether a chromosome abnormality caused the miscarriage cannot change what has happened, but an answer can ease self-blame and help with planning a future pregnancy. Testing is a personal choice, and deciding not to test is just as valid.

With a missed miscarriage, timing matters. Because the pregnancy is still in the womb, there may be days or weeks between diagnosis and treatment: time to decide whether you want testing and to plan how it would be done. Our guide to genetic testing before miscarriage treatment covers this window in detail.

01

Testing the pregnancy tissue

Pregnancy tissue can be tested after surgical or medical management, or sometimes after a miscarriage at home if the tissue is collected. Many laboratories now use a chromosomal microarray, which analyses the DNA directly without needing cells to grow; older karyotyping needs living cells and fails in about 1 in 5 samples.

For a usable result, the tissue needs to reach the laboratory fresh, in a sterile container and without preservative. Tissue that has been put into formalin, the preservative normally used when tissue is examined under a microscope, is generally unsuitable. If you would like testing, tell your team before treatment so that a fresh sample can be set aside.

In the UK, RCOG guidance recommends offering chromosome testing of the tissue from a third or later miscarriage, or any miscarriage in the second trimester; NHS laboratories also accept tissue when there are particular features, such as a structural abnormality seen on a scan. Otherwise it is not usually offered after a first or second early loss, though some people arrange it privately. Read more about pregnancy tissue testing.

02

A blood test before treatment

As long as pregnancy tissue remains in the womb, placental cells keep shedding small fragments of DNA into the mother's blood. A blood test can analyse this cell-free DNA to look for extra or missing chromosomes without needing any tissue. Because the DNA comes from the placenta, the result usually, but not always, reflects the pregnancy itself.

Timing is critical. In a Danish study of 1,463 women, about 1 in 11 blood tests gave no result while the tissue was still in the womb, rising to more than 1 in 4 when blood was taken 12 to 24 hours after the tissue had passed. A scan shortly before the sample helps confirm that the pregnancy is in the womb and that the tissue is still there.

Across eight studies of 552 miscarriages, the blood test found about 78 in 100 of the extra or missing chromosomes that tissue testing identified, and gave a correct normal result in about 91 in 100 pregnancies with the usual number of chromosomes. Triploidy was left out of these figures because the usual counting methods cannot detect it; they also miss balanced rearrangements and very small changes, so the result is a screening-type answer rather than a definitive diagnosis.

Blood-based testing after miscarriage is newer than tissue testing and is still being studied; NHS testing after miscarriage uses pregnancy tissue. We do not offer a bookable blood test for this online, but our genetic counsellors can explain the options. Compare the two approaches in blood test or tissue test.

03

What a result can and cannot tell you

If a chromosome abnormality is found, it usually means the miscarriage happened by chance and was not caused by anything you did. RCOG guidance notes that finding a chromosome abnormality in a miscarriage is linked with a better outlook in the next pregnancy than a loss with normal chromosomes, for women of the same age.

A normal result means no chromosome cause was found for that pregnancy; it does not rule out other causes. A 'normal female' result from older karyotyping can sometimes reflect the mother's own cells rather than the pregnancy's, which SNP-based microarrays can check for. If a result shows an unbalanced rearrangement, both partners may be offered a parental karyotype blood test.

Now and then the result points to a partial molar pregnancy, which calls for a period of hormone (hCG) monitoring; our molar pregnancy page explains why. Our guide to understanding your result explains the common findings; for complex results, a clinical genetics consultation is available.

Your options

Before you choose medical or surgical management

If you have no heavy bleeding, severe pain or signs of infection, there is usually time to think. Your physical health rarely depends on choosing quickly, although it is completely understandable to want to move forward soon for emotional reasons.

Check that the diagnosis has been confirmed in line with NICE guidance, with a repeat scan or second opinion where needed, and ask about anything that is unclear.

Decide whether you would like to know if there was a chromosomal cause. Some testing options close once the pregnancy has passed, so it helps to decide before treatment starts.

If you want tissue testing, ask your team to set aside a fresh sample without preservative, and find out whether you qualify for NHS testing.

A blood-based test only works well before the pregnancy has passed, so the sample is taken before treatment, ideally shortly after a scan.

Give yourself time. Talking it through with a genetic counsellor before treatment can help you decide whether testing feels right for you.

Treatment

Your options for managing a missed miscarriage

Once a missed miscarriage has been confirmed, you will be offered a choice of how to manage it. The choice is entirely personal, and there is no single right option for everyone. Your team should explain the benefits, risks and practical side of each, taking into account your preferences, medical history and circumstances.

Usually offered first

Expectant management (waiting)

Waiting for the body to recognise the loss and miscarry naturally. NICE recommends offering this first, usually for 7 to 14 days, except where heavy bleeding is more likely or would be more dangerous, where a previous pregnancy experience was traumatic, or where there are signs of infection. Some people value letting nature take its course; for others the wait, which can be several weeks with a missed miscarriage, is too hard. Tissue passed at home can sometimes be collected for testing.

Often at home

Medical management (tablets)

Medication makes the womb contract and pass the pregnancy tissue. For a missed miscarriage, NICE recommends a mifepristone tablet followed 48 hours later by misoprostol; older advice used misoprostol alone. It usually takes place over several days and can often be managed at home, with support and follow-up. If no bleeding has begun within 48 hours of taking misoprostol, let your unit know. A blood-based test, if you want one, is normally done before treatment starts.

Most predictable timing

Surgical management

A minor procedure to remove the pregnancy tissue, sometimes still called evacuation of retained products of conception (ERPC). It can be done either in a clinic, using manual vacuum aspiration with a local anaesthetic, or in an operating theatre while you are asleep under a general anaesthetic. It is usually completed within a day, but carries the small risks of any procedure. If you would like testing, ask in advance for tissue to be sent fresh to a genetics laboratory.

Timing

How long can a missed miscarriage take to pass naturally?

Left to happen naturally, a missed miscarriage can take days or weeks to pass. The figures below come from a UK early pregnancy unit study of 138 women with a missed miscarriage who chose to wait. Times are counted from the diagnosis, and the pregnancy may have stopped developing some time before that.

Time since diagnosisHad passed without treatment
1 weekAbout 3 in 10
2 weeksAbout 6 in 10
About 6 weeksAbout 3 in 4

The remaining women had surgery to remove the tissue; tablets were not one of the options in this study. NICE advises a home urine pregnancy test 3 weeks after expectant or medical management, and further assessment if the test is still positive or if bleeding has not started or keeps going.

Choosing what feels right for you

Your healthcare team should talk through all three options with you. Serious problems, such as infection, are uncommon with all three, and your chance of a healthy pregnancy in the future is much the same whichever you choose.

Some people decide straight away; others need a few days to take in the news first, and both are fine. If waiting becomes too difficult, talk to your early pregnancy unit about switching to another option. Contact them straight away if you develop heavy bleeding, severe pain or a high temperature.

Emotional support

When the news comes out of nowhere

The emotional impact of a missed miscarriage can be particularly intense because it is so unexpected. Unlike losses where symptoms gave some warning, it usually comes as a shock during what should have been a routine, reassuring appointment.

Many women describe feeling confused, or betrayed by their bodies. You may wonder how long ago the pregnancy stopped developing, or feel distressed that you carried on feeling pregnant and taking pregnancy vitamins. Shock, sadness, anger, guilt and anxiety about future pregnancies are all normal. It may help to know that there was usually nothing you could have done to prevent the loss or to detect it sooner.

There can be practical challenges too, such as telling family, friends or an employer who knew about the pregnancy. You may need time off work, both for the physical miscarriage and for emotional recovery.

Support is available from your healthcare team, counselling services and pregnancy loss support groups, and many people find it helps to talk to others who have been through the same thing. For support, you can call Miscarriage UK on 0303 003 6464 or speak free to a Tommy's midwife on 0800 0147 800. In England, parents can apply for a baby loss certificate to recognise a loss before 24 weeks.

At London Pregnancy Clinic, our team knows how much a careful, unhurried examination and clear, compassionate communication matter at this point. We aim to give you an accurate diagnosis, full information about your options and ongoing support, whichever path you choose.

Cupped hands gently holding a pale flower
Shock, sadness and guilt are all common reactions to a missed miscarriage diagnosis

Alongside your NHS care

Where our clinic fits in

Your NHS early pregnancy unit confirms the diagnosis, discusses your options and provides treatment free of charge. Our services sit alongside that care if you would like a second look at a scan, time with a genetic counsellor, or testing the NHS does not routinely offer after one or two miscarriages. We see patients in the City of London and West London; genetic counselling is online.

Online, 30 minutes

Genetic counselling

An online consultation with a registered genetic counsellor about whether testing is still possible, which approach could fit your situation and what a result might mean.

If the diagnosis is uncertain

Second-opinion scan

From around 10 weeks, a specialist rescan with Dr Fred Ushakov, with an explanation of the findings, before you make decisions about treatment.

Arranged through counselling

Pregnancy tissue testing

Not booked online. Speak to a genetic counsellor, ideally before treatment, so that fresh tissue can be collected and sent to the laboratory.

Missed miscarriage: common questions

Is a missed miscarriage the same as a blighted ovum?

Not quite. A blighted ovum, better called an anembryonic pregnancy, is one type of missed miscarriage in which the sac develops but no embryo is seen. In other missed miscarriages an embryo or fetus is visible but has no heartbeat. Both are often caused by a chance chromosome abnormality. Read more in our guide to anembryonic pregnancy.

Could I have known that my pregnancy had stopped developing?

Usually not. Pregnancy hormone levels often remain high for a while after development stops, so symptoms often carry on and home tests stay positive. In most cases an ultrasound scan is the only way to find out. Not noticing does not mean you missed something or did anything wrong.

How long ago did the pregnancy stop developing?

The measurements on your scan give a rough idea, because they show the size the pregnancy reached. It may have stopped developing days or several weeks before the scan. Why some miscarriages begin quickly while others take much longer is not understood. Your sonographer or early pregnancy unit can talk you through what your own scan showed.

Can genetic testing still be done if the miscarriage has already passed?

Possibly. If tissue was collected and kept fresh, without preservative, it may still be testable. A blood-based test is much less likely to work once the tissue has passed, because placental DNA in the blood falls over the following hours and days. If no tissue was tested, a genetic counsellor can advise on what else may help. See what can I test now? for the options at each stage.

Will I need a check that the miscarriage is complete?

After expectant or medical management, NICE advises a home urine pregnancy test 3 weeks later. If it is still positive, or bleeding has not started or keeps going, your early pregnancy unit will reassess you, which may include a scan. Some people also choose a post-miscarriage scan after their first period to see how the womb has recovered.

About this information

The information on this page is for general education about missed miscarriage and is no substitute for personal advice from the clinicians caring for you. If you have heavy bleeding, severe pain or a high temperature, or you feel faint or very unwell, contact your early pregnancy unit or NHS 111 without delay; in an emergency, call 999.

Contact

Questions after a missed miscarriage diagnosis?

Send us an enquiry

This form is not monitored for emergencies. For heavy bleeding, severe pain or feeling faint, call 999 or go to A&E.

For urgent matters please call 020 3687 2939.

Sources & clinical references

The figures and clinical statements on this page are drawn from the sources below. Guidance evolves — always discuss your individual circumstances with a clinician.

  1. NICEEctopic pregnancy and miscarriage: diagnosis and initial management (NG126) — diagnosis of viable intrauterine pregnancy2026
  2. NICEEctopic pregnancy and miscarriage: diagnosis and initial management (NG126) — management of miscarriage2026
  3. RCOGRecurrent Miscarriage (Green-top Guideline No. 17)2023
  4. The Lancet (Quenby et al.)Miscarriage matters: the epidemiological, physical, psychological, and economic costs of early pregnancy loss (accepted manuscript)2021
  5. Scientific Reports (Xue et al.)Genetic analysis of chorionic villus tissues in early missed abortions2023
  6. BMJ (Luise et al.)Outcome of expectant management of spontaneous first trimester miscarriage: observational study2002
  7. Prenatal Diagnosis (Pauta et al.)Genome-wide cell-free DNA analysis for aneuploidy detection in miscarriages: test performance meta-analysis2025
  8. Human Reproduction (El Sammaa-Aru et al.)How big is the time window for cell-free fetal DNA testing after pregnancy loss and which factors are associated with a successful result?2026
  9. North West Genomic Laboratory Hub (Manchester University NHS Foundation Trust)Acceptance criteria and requirements for solid tissue samples following loss of pregnancy2025
  10. Tommy'sMissed (silent) miscarriage: information and support2026
  11. Miscarriage UK (The Miscarriage Association)Missed miscarriageAccessed October 2026
  12. Miscarriage UK (The Miscarriage Association)Causes and risk factors of miscarriageAccessed October 2026